Condition
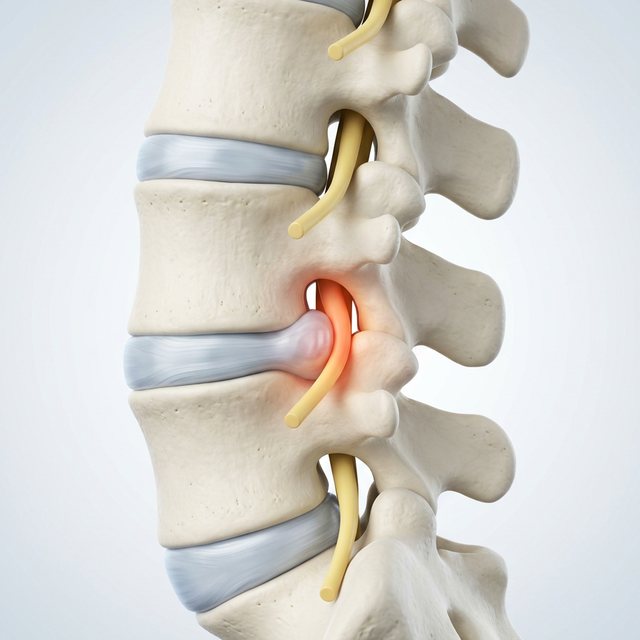
Disc material pressing on nearby nerves.
We’re closed right now. WhatsApp us and we’ll reply when we open.
- Registered Chiropractor 註冊脊醫
- Doctor of Chiropractic D’Youville College, USA
- Whampoa & Hung Hom Near Whampoa MTR
A herniated disc, also called a slipped or prolapsed disc, is when the soft centre of a spinal disc pushes out through a tear in its tough outer ring. It is most common in the lower back and the neck, and causes pain when it presses on or irritates a nearby nerve, often with pain, tingling or numbness down a leg or an arm. Most herniated discs settle without surgery over weeks to months. Numbness around the groin, a change in bladder or bowel control or weakness that is getting worse needs prompt medical attention.
Key points
- A disc in the lower back usually causes back and leg symptoms (sciatica); a disc in the neck causes neck and arm symptoms.
- Discs that bulge or herniate are common on scans in people with no pain at all, so the scan has to match your symptoms.
- Most cases improve with time, staying active and non-surgical treatment; surgery is considered for severe or persistent symptoms or worsening weakness.
- Numbness around the groin, bladder or bowel changes, or weakness in an arm or leg that is getting worse need prompt medical attention.
Between each pair of vertebrae sits a disc: a tough outer ring of layered fibres (the annulus) around a soft, jelly-like centre (the nucleus). Discs absorb shock and let the spine bend and twist. With age and repeated strain, the outer ring can weaken and develop small tears.
In a disc bulge, the disc spreads a little beyond its normal edge all round. In a herniation, part of the nucleus pushes out through a tear, usually towards the back and to one side, where the nerve roots leave the spine. The pressure and the chemical irritation from the disc material can inflame the nerve. Herniations are most common at the bottom two levels of the lower back and in the lower neck.
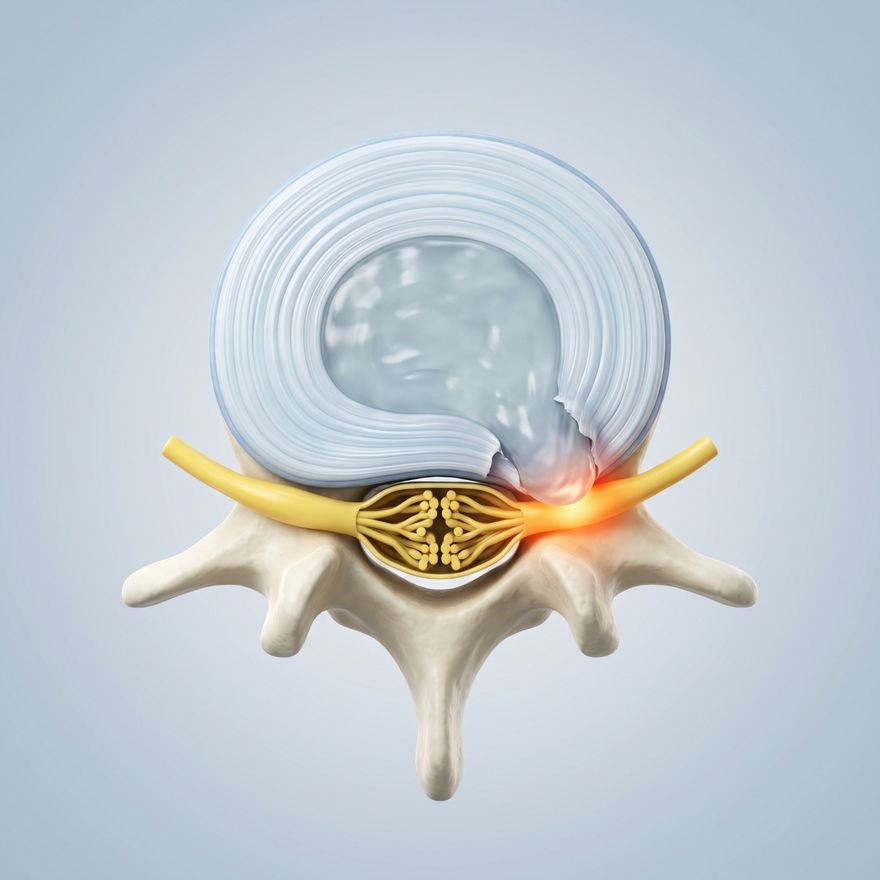
Symptoms depend on where the disc is and which nerve it irritates. Some herniated discs cause no symptoms at all.
Common symptoms
- Lower back or neck pain, often with stiffness and difficulty bending or turning
- Pain that travels into the buttock and down a leg (sciatica), or from the neck into the shoulder blade and arm
- Tingling, pins and needles or numbness in the leg, foot, arm or hand
- Weakness in the muscles supplied by the nerve, such as a weak grip or difficulty lifting the front of the foot
- Pain that is worse with sitting, bending, coughing or sneezing
How it usually progresses
Most herniated discs follow a broadly similar course:
- First weeksPain is often at its worst, especially sitting and bending. Gentle movement usually helps more than rest.
- 6 to 12 weeksMany people improve steadily as the irritation settles, and the herniated material often shrinks over the following months.
- After 3 monthsPain, numbness or weakness that persists or gets worse needs a fresh assessment, and sometimes a scan or a surgical opinion.
Symptoms don’t always follow this order, and a disc can flare up again, so recovery usually includes exercises and changes to sitting and lifting.
A herniation often follows a lift or a bend, but it usually reflects changes in the disc that have built up over time.
- Age-related changes that dry out and weaken the disc, most often between the ages of 30 and 50
- Lifting, especially heavy loads held away from the body or with a twist
- Long periods of sitting or driving, and repeated bending
- Being inactive or overweight, which increases the load on the discs
- Smoking, which reduces the disc’s blood supply and weakens its tissue
- A family history of disc problems
Disc bulges are found on MRI scans in about a third of people in their twenties with no back pain, and in more than half of those over 50.
These two simple checks can help you describe your symptoms, but they cannot confirm a diagnosis. Stop if anything causes sharp or spreading pain.

Is it worse sitting than walking?
Compare how you feel after 20 to 30 minutes of sitting with a short, easy walk. Pain that builds with sitting, bending or coughing and eases when you stand up and walk fits a disc pattern. Leg pain that comes on with walking and eases when you sit down or bend forward suggests narrowing of the spinal canal instead.

Do you have symptoms in an arm or a leg?
Note whether pain, tingling or numbness spreads beyond the spine: from the lower back into the leg and foot, or from the neck into the arm and hand. Symptoms in a limb, especially with weakness, suggest a nerve root is involved; see Sciatica and Hand numbness.
These checks can’t rule other causes in or out. If symptoms last more than a few weeks, keep coming back or come with weakness, have them properly assessed by a healthcare professional.
Several problems can cause similar pain. Finding where it comes from is the key to choosing the right treatment.
Herniated disc (the soft centre of a disc pressing on a nerve)
- Where it usually hurts
- The lower back or neck, often spreading down one leg or arm
- Other clues
- Worse sitting, bending, coughing or sneezing; tingling or numbness along the nerve
Spinal stenosis (narrowing of the spinal canal)
- Where it usually hurts
- Both legs or one, sometimes with an aching back
- Other clues
- Comes on with walking or standing; eases when sitting or bending forward; more common over 60
Facet joint or muscle strain
- Where it usually hurts
- The back or neck, sometimes into the buttock or shoulder, usually not below the knee or elbow
- Other clues
- Stiffness; often worse leaning backwards or turning; no numbness
Bone spurs narrowing a nerve’s exit
- Where it usually hurts
- The neck or lower back, with arm or leg symptoms
- Other clues
- Usually older adults; symptoms build gradually rather than after a lift
Shingles can also cause burning pain along one nerve, usually followed by a rash a few days later.
Further reading: Sciatica, Bone spurs, Neck pain.
Diagnosis relies mainly on your history and a physical examination. A scan is needed only in some cases.
Your history: Where the pain and numbness go, what makes them better or worse, and how they started, with questions to check for warning signs.
Physical examination: Checking how your spine moves and testing the strength, reflexes and sensation in your arms or legs, to work out which nerve root is involved.
Further tests: An MRI scan may be needed if symptoms are severe or getting worse, there is weakness, or surgery or an injection is being considered. If needed, Dr. Ho will refer you for a scan or to an orthopaedic doctor.
Most herniated discs settle without surgery. Treatment usually aims to ease the pain and nerve irritation, keep you moving, and then rebuild strength.
Non-surgical treatment
- Cox flexion-distraction (spinal decompression): A gentle, rhythmic technique on a special table that flexes and stretches the lower back, often considered for disc-related back and leg pain.
- Staying active: Keeping up daily activities and walking as far as you comfortably can, rather than bed rest, with short rests when needed.
- Exercise and rehabilitation: Exercises that ease the nerve symptoms, then strengthen the trunk, hips or neck, built up gradually under guidance.
- Spinal mobilisation and adjustment: Gentle hands-on techniques chosen to suit disc-related pain, which may ease pain and stiffness for some people.
- Soft tissue treatment: Releasing muscles that tighten around the painful area, which may ease pain in the short term.
Treatment prescribed by a doctor
- Medication or injections: Anti-inflammatory painkillers may ease pain in the short term, but don’t suit everyone, so check with a doctor or pharmacist. For severe nerve pain, a specialist may offer a steroid injection around the nerve, which may ease pain for a time.
Surgery
- Discectomy: Removing the part of the disc pressing on the nerve, often through a small incision. It may be considered for severe pain that persists after several weeks of non-surgical treatment, or for weakness that is getting worse. Bladder or bowel problems need emergency surgery.

Dr. Ho first works out which disc and nerve are involved, then plans treatment based on the findings. General information only — your plan is set after an in-person assessment.
- 01
Assess
Examining your spine and testing the nerves to your arms or legs, to find the source of the pain and check for anything that needs a doctor’s attention.
- 02
Treat
Gentle, disc-focused techniques such as Cox flexion-distraction (spinal decompression), chosen to suit your assessment.
- 03
Exercise and habits
Exercises that ease the nerve symptoms, building to strengthening, with advice on sitting, lifting, sleeping and keeping active.
- 04
Refer
If there is weakness, symptoms don’t improve, or a scan, injection or surgical opinion may be needed, you will be referred to a doctor or for imaging.
Regular movement and strength help keep discs healthy, and help stop a disc problem coming back.
- Walk regularly: walking is often comfortable with a disc problem and keeps the spine moving.
- Break up sitting every 30 to 60 minutes, and avoid long periods slumped on a sofa or bent over a phone.
- Exercise regularly to strengthen the trunk, hips and neck; swimming, yoga and pilates may also help.
- Lift with the load close to your body, bend at your hips and knees, and don’t twist as you lift.
- Keep to a healthy weight, and don’t smoke.
- During a flare-up, ease off sitting and bending rather than stopping everything, then build back up gradually.

When to seek medical attention promptly
Seek medical attention promptly if any of the following apply:
- Numbness around the buttocks, genitals or inner thighs (go to A&E immediately)
- New difficulty passing urine, or loss of bladder or bowel control (go to A&E immediately)
- Weakness, numbness or tingling in both legs, or in one leg that is getting worse
- Arm or hand weakness that is getting worse, clumsy hands, or unsteady walking
- Pain after a significant fall or accident
- Pain with a fever, unexplained weight loss, a past history of cancer, or constant pain that is worse at night
Often, yes. Many people improve over weeks to a few months as the irritation settles, and the herniated part of the disc often shrinks with time. Staying active and the right exercises may help. Weakness, or symptoms that keep getting worse, need prompt assessment.
Usually not. Surgery may be considered if severe pain persists after several weeks of non-surgical treatment, or if weakness is getting worse, and is needed urgently if bladder or bowel control is affected.
Chiropractors commonly assess and treat disc-related pain, using gentle techniques chosen to suit the disc, such as flexion-distraction, together with exercise and advice. Dr. Ho will check whether care is suitable for you, and refer you to a doctor if there are signs that need one.
It is often considered for disc-related back and leg pain, and some studies suggest it may help ease pain, but it doesn’t suit everyone. It may not be suitable after some spinal surgery, with severe osteoporosis or with worsening weakness. Dr. Ho checks this at your first visit.
Yes, within comfort. Walking and gentle exercises usually help, and strengthening comes later. Ease off heavy lifting, deep bending and anything that sends pain down a leg or an arm, and build back up gradually.
Disclaimer
This page is general information only, not a diagnosis or treatment advice. If you have any symptoms, please consult a qualified healthcare professional.
Treatment
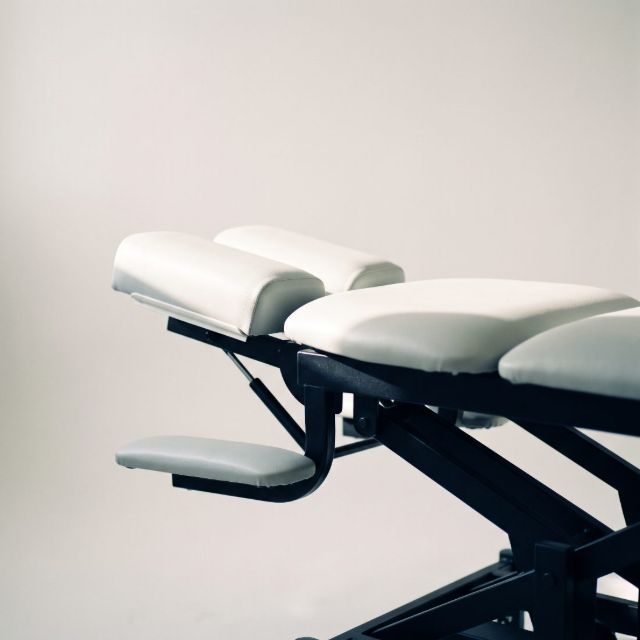
Spinal Decompression
Gentle, controlled traction using a Cox flexion/distraction table to relieve pressure on the spine and discs.Read more
Chiropractic Spinal Adjustments
Hands-on, targeted adjustment of spinal and joint restrictions to help restore normal movement.Read more
Rehabilitation
Guided exercises to rebuild strength, stability, and mobility, and help reduce the chance of recurrence.Read more
Book a consultation with Dr. Ho, or message us on WhatsApp with any questions first.